Forms CA-17 and CA-20, box by box
The CA-17, the duty status report, arrives by fax with Side A already filled in by a federal employee’s supervisor. Side B is yours, and the instructions give you two days before your patient’s pay is interrupted. The CA-20, the attending physician’s report, follows, and one box on it decides whether the claim is accepted at all.
- Jump to
- Form CA-17 or Form CA-20
- Forms
- CA-17, Duty Status Report (Rev. 04/2020) and CA-20, Attending Physician’s Report (Rev. 08/2023)
- Issued by
- U.S. Department of Labor, Office of Workers’ Compensation Programs
- OMB control number
- 1240-0046, expiry printed as 08/31/2026, which has passed, so I would check dol.gov for a newer copy before printing
- CA-17 goes to
- the patient’s federal employer, within 2 days; a copy to OWCP
- CA-20 goes to
- OWCP, by post or uploaded through ECOMP
- Who may sign
- a physician; a nurse practitioner or physician assistant needs a physician’s co-signature
Key points
- The CA-17 asks what your patient can do and goes to the employer within two days.
- The CA-20 asks whether work caused it and goes to the federal workers’ comp office.
- CA-17 item 13: “yes” means regular duty, “no” means you fill in the restrictions.
- CA-20 item 9: a yes needs a sentence on how work caused it, or it is not accepted.
- “Pain” is not a diagnosis. List it as a symptom of the condition you name.
- A nurse practitioner or physician assistant needs a physician to co-sign.
Before you start: two forms, two questions
These are the two forms a federal employee brings you after an injury at work. The federal government runs its own workers’ compensation programme, under a law called the Federal Employees’ Compensation Act (FECA), and the office that runs it is the Office of Workers’ Compensation Programs (OWCP). Both forms are OWCP’s, but they answer different questions and go to different places.
The CA-17, the Duty Status Report, asks one thing: can your patient work, and if not fully, what can they do? Their supervisor fills in Side A, describing the job, and sends it to you. You fill in Side B and return it to the employer within two days. The instructions say that deadline is there so the employee’s income is not interrupted. A copy goes to OWCP.
The CA-20, the Attending Physician’s Report, asks what happened and whether work caused it. It goes to OWCP, and OWCP will not pay your patient for lost wages until it has a medical report. It is short, one page of questions, and one of them, item 9, decides the claim.
Under this programme, medical evidence has to come from a physician. The CA-20 says so under its signature line. It says that if the treating provider is not a physician, such as a nurse or a physician assistant, a physician has to co-sign, and it gives a line for that. The CA-17 has no such line. It has one block, item 19, headed Physician’s Signature, and I have not found anything printed on it that says how a co-signature should be added. If a nurse practitioner or physician assistant completed the CA-17, I would ask the agency or OWCP how they want it signed before sending it.
The rule: 5 U.S.C. § 8101 and following; the instructions printed under the CA-20’s signature line.
Form CA-17, the Duty Status Report
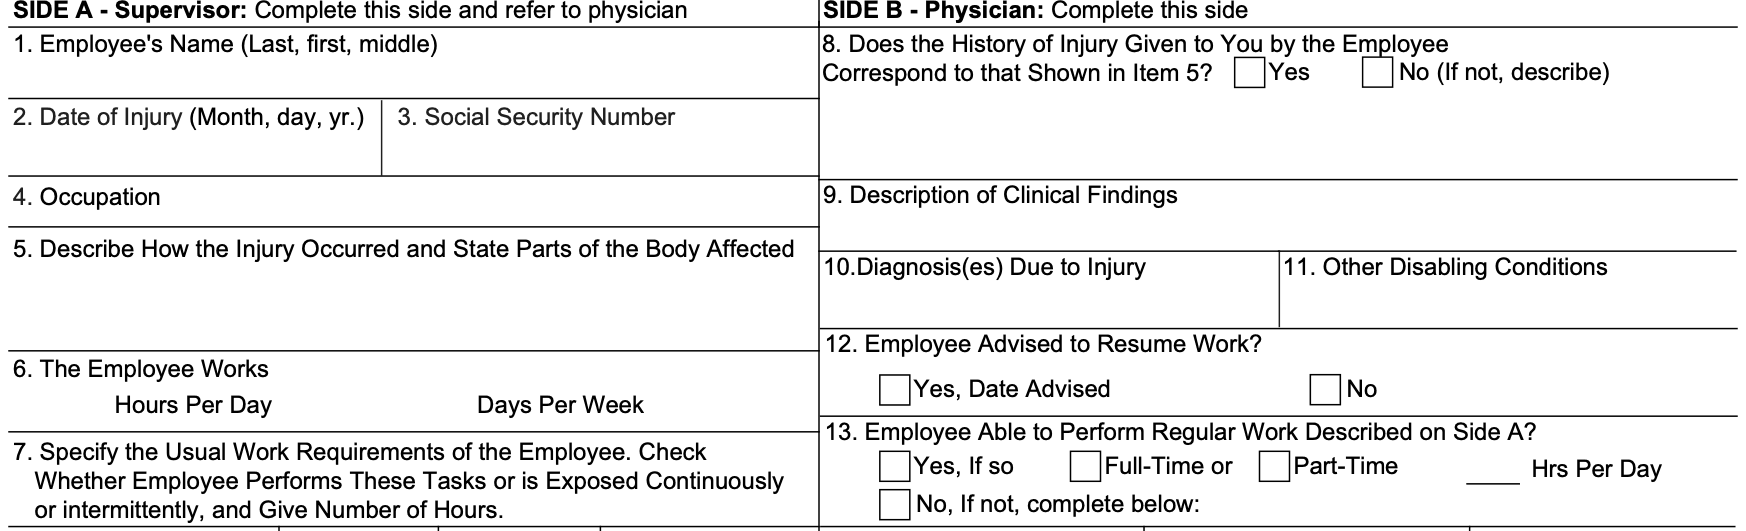
The supervisor fills in Side A, you fill in Side B, and it goes back to the employer within two days. The sections below follow the form’s own item numbers. If you need a clean copy, the blank CA-17 is on the Department of Labor’s site.
Side A: what the supervisor gave you
Employee name, date of injury, occupation, how the injury occurred and the parts of the body affected, the usual hours per day and days per week, and item 7, the physical requirements of the job: lifting with the maximum weight, sitting, standing, walking, climbing, kneeling, bending, twisting, pushing and pulling, grasping, fine manipulation including keyboarding, reaching above the shoulder, driving, operating machinery, temperature extremes, humidity, chemicals, fumes and noise, each marked continuous or intermittent with hours per day.
That table is the reference for everything you write on Side B. Your restrictions column sits beside it, line for line, so that the employer can compare what the job needs with what your patient can do. If Side A is blank, you are certifying against a job you have not been told about. I would ask the employer for it, or fill in what my patient tells me the job involves and say that is where it came from.
Item 8: does the history match?
Does the story your patient told you match what the supervisor wrote in item 5? Check yes or no, and if no, describe the difference. I think of this box as a credibility check on both accounts. A “no” is not an accusation. Writing “the employee reports the lift was from floor level, item 5 says from a table” is exactly what the box is for. What does not help is a “yes” over a history that your own findings box then contradicts.
Items 9 to 11: findings, the diagnosis due to the injury, and everything else
Item 9 asks for your clinical findings: what you saw on examination and what testing showed, with dates. Item 10 asks for the diagnosis due to this injury, and item 11, other disabling conditions, is where everything that is not due to this injury goes. Keep the two apart. A patient with a lumbar strain from a lift and long-standing knee arthritis has a strain in item 10 and arthritis in item 11. If the arthritis goes in item 10, the examiner has to work out which part of the disability the employer is responsible for, and the form will probably stall while they ask.
The findings box is the evidence for the restrictions you are about to certify. “Low back pain” with nothing under it does not support a lifting limit. A finding such as “paraspinal spasm and tenderness at L4 to L5, straight-leg raise positive on the right at 40 degrees, no neurological deficit” does.
Items 12 and 13: can they work, and what can they do?
Item 12 asks whether you have advised your patient to go back to work, and on what date. Item 13 is the decision: can your patient perform the regular work described on Side A? Check yes, full time or part time with hours per day, and you are done with the table. If you check no, the form asks you to “complete below”, which is the restrictions column on Side B. I go down the supervisor’s list in item 7, and for each activity I write whether my patient can do it continuously or only now and then, for how many hours a day, with a weight limit for lifting and a temperature range where that applies.
Fill in the column as what your patient can do, not what they cannot. The employer uses it to build a light-duty assignment: “lifting up to 10 pounds, intermittent, 2 hours per day; sitting continuous, 6 hours; no climbing” is a job someone can be given. The form says to complete the restrictions when you check no. A “no” with the column left blank does not do that, because it tells the employer only that the employee cannot do their job, not what they could be offered instead.
Item 14 asks whether a neuropsychiatric condition affects your patient’s ability to give or take supervision or meet deadlines; answer it only when there is one. Items 15 and 16 are the date of this examination and the next appointment, and the next appointment is read as the date the restrictions will be reviewed. Then your specialty, tax identification number, signature and date in items 17 to 20, your name and address in the box at the foot, and back to the employer within two days.
Form CA-20, the Attending Physician’s Report
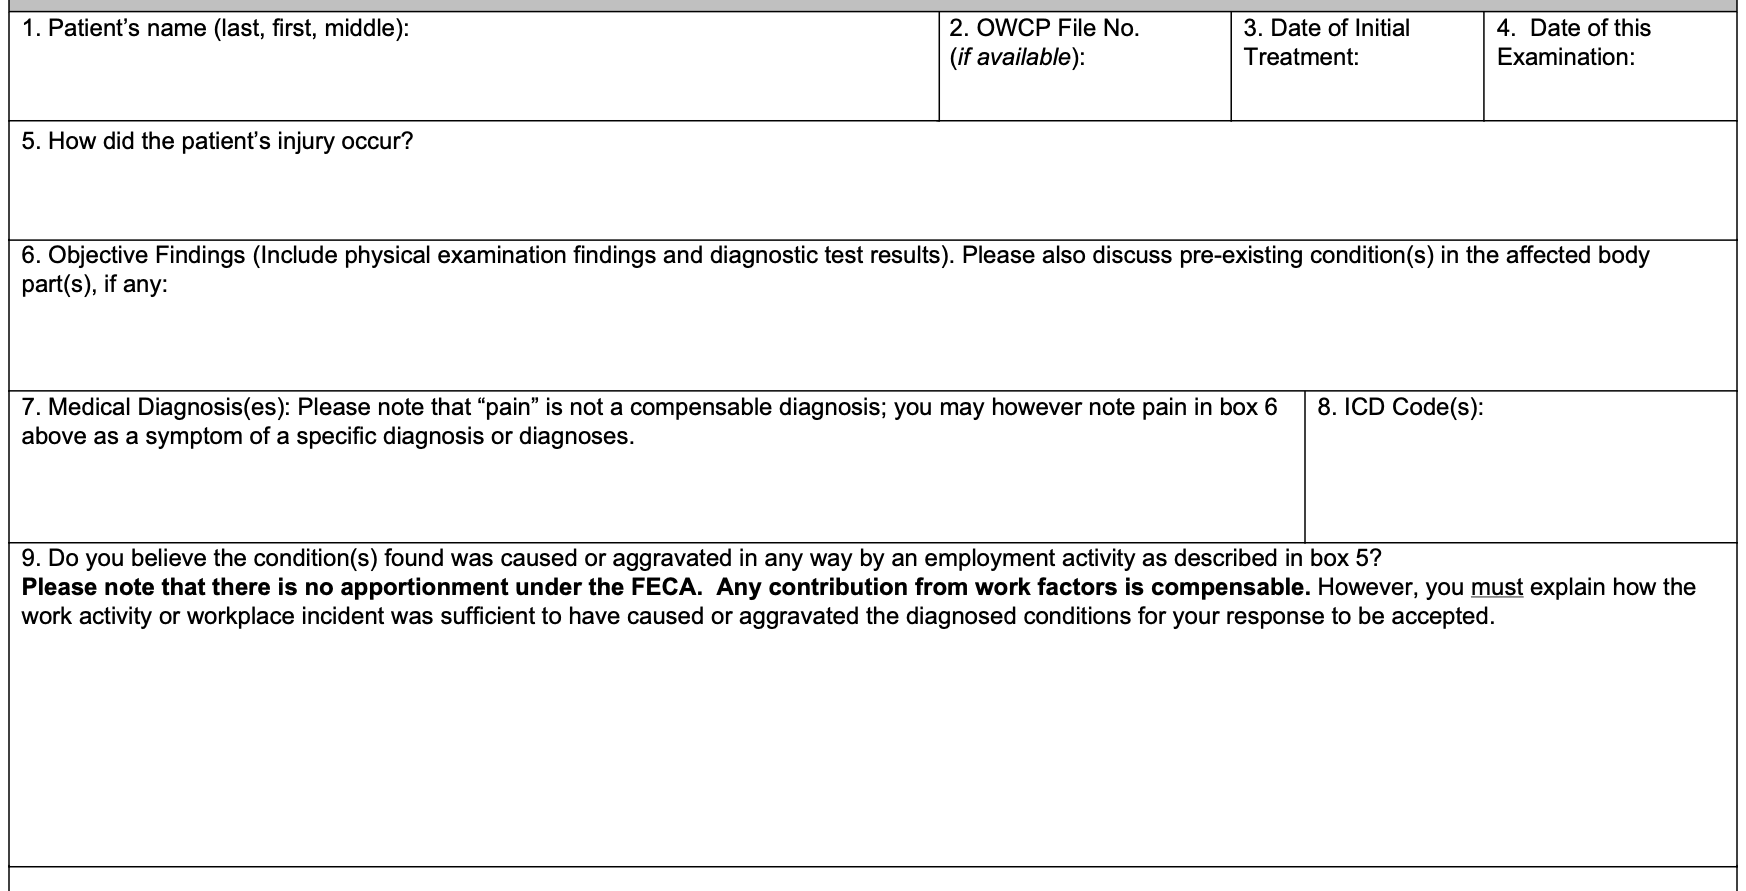
The CA-20 goes to OWCP, not the employer, and it is the medical report the claim is decided on. The sections below follow its item numbers, and the blank CA-20 is on the Department of Labor’s site.
Items 1 to 5: who, when, and how it happened
Where the CA-17 answers “can this person work”, the CA-20 answers “what happened, and is it work-related”. Items 1 to 4 are the patient’s name, the OWCP file number if your patient has one (leave it blank if not), the date your patient first sought treatment for this injury, and the date of the examination your answers are based on.
Item 5 asks how the injury occurred. Write the mechanism in your patient’s words and as specifically as you can: the weight lifted and from where, the fall and onto what, the repetitive task and for how long. This box is what item 9 will have to connect to the diagnosis, so a vague item 5 (“injured back at work”) leaves item 9 with nothing to explain.
Item 6: what you found, including what was already there
Your findings on examination and any test results, as related to the injury in item 5. The form then asks for something the CA-17 did not: any pre-existing condition in the affected body part. Do not leave it out to protect the claim. Under this programme a work injury that worsens an existing condition is still covered, and the instructions say so. What the examiner needs is to know the condition was there, so that item 9 can say the work aggravated it. A pre-existing condition that turns up later in the records, unmentioned here, is what damages the claim.
Items 7 and 8: the diagnosis, and why “pain” is not one
Item 7 asks for the specific diagnosis of each condition connected to the injury, and item 8 for the ICD code for each. The form prints its own warning in item 7: “pain” is not a compensable diagnosis. Lumbar pain, shoulder pain and knee pain are symptoms, and a CA-20 with one of them in item 7 is not accepted. Name the condition (lumbar strain, rotator cuff tear, medial meniscus tear) and put the pain in item 6, as the form suggests, as a symptom of it. If you do not yet have a diagnosis, say what you have (“acute lumbar strain, imaging pending”) rather than leaving the box to a symptom.
Item 9: did work cause it, and the sentence the form wants
Do you believe the condition was caused or aggravated in any way by the work activity described in item 5? This is the box that decides whether the claim is accepted. The form says two things in bold. First, there is no apportionment: if work contributed at all, the condition is covered, so you are not being asked to weigh work against everything else. Second, you must explain how the work activity was sufficient to cause or aggravate the diagnosis, or your answer is not accepted. A yes with nothing after it does not meet what the form asks.
One or two sentences that connect item 5 to item 6 to item 7 is what is being asked for: “Lifting a 60-pound parcel from floor level with a twist, as described in item 5, is a mechanism sufficient to cause the lumbar strain diagnosed in item 7; the paraspinal spasm and positive straight-leg raise in item 6 are consistent with it, and there was no prior back complaint.” The instructions name four kinds of connection, and using the word helps the examiner: direct causation (the work caused the condition), aggravation (the work made an existing condition worse, and you say whether temporarily or permanently, and if temporarily, when it ended or will end), acceleration (the work brought the condition on faster than its natural course), and precipitation (a condition that would have stayed silent but for the work). A later injury that follows naturally from the first, such as a fall caused by the injured knee giving way, is covered too, and can be noted here.
The rule: the instructions for box 9, printed on page 2 of the CA-20.
Items 10 to 12: how disabled, from when, and what they could do
Item 10 asks you to circle one of three, and the instructions define them. Totally disabled means your patient cannot do any work at all. Give the date it began and the date you expect them back at full or modified work. Partially disabled means they cannot do the job they held when injured but can do some work. Give the date it began and the expected return to full duty, and complete item 11. Not disabled means they can do the job they held, and the form asks whether there was any disability earlier in the case and its dates.
Item 11, for a partial disability, asks for the extent of the physical limitations and the type of work that could reasonably be done within them, in the same numbers as the CA-17 column. If you would rather give the capacity separately, the form points you to OWCP-5c, the Work Capacity Evaluation, and the instructions name the psychiatric and cardiac versions too. Item 12, remarks, is for anything else about this injury; if there is nothing, leave it blank.
Signing it, and where it goes
Item 13 is the certification and the signature, with a second line beneath it: if the treating provider is not a physician, a physician signs there too. The instructions add that, under this programme, a clinical psychologist counts as a physician within their scope, and a chiropractor only for a spinal subluxation shown on x-ray. Items 14 to 17 are your name, address, tax identification number and specialty.
The CA-20 goes to OWCP, not to the employer: by post to the address on page 3, or uploaded through the ECOMP portal, which gives you a tracking number so you can confirm it arrived. The bill goes on the OWCP-1500, not attached to the form. The CA-17 goes the other way, to the employer, within two days, with a copy to OWCP. If either one goes to the other’s address, it can easily cost your patient a week.
Why it may not be accepted
- CA-20 item 9 says yes with no explanation of how the work caused or aggravated the condition.
- “Pain” is entered as the diagnosis in item 7.
- CA-17 item 13 is “no” and the restrictions column is blank.
- Signed by a nurse practitioner or physician assistant with no physician co-signature.
- The CA-17 sent to OWCP instead of the employer, or after the two days.
Questions the office asks
Who completes Side A of the CA-17, and who completes Side B?
The patient’s supervisor completes Side A, which describes the job, and refers the form to you. You complete Side B, sign it and return it to the employing agency within two days. If Side A arrives blank, ask for it, or write down what your patient tells you the job involves and say that is where it came from.
Can a nurse practitioner or physician assistant complete these forms?
They can complete them, but under this programme the report only counts if a physician co-signs it. The CA-20 has a second signature line for exactly that. A clinical psychologist counts as a physician within their scope, and a chiropractor only for a spinal subluxation shown on x-ray.
Where does the CA-20 go?
To OWCP, never to the employer. Post it to the address printed on the form (PO Box 8311, London, KY 40742-8311), or upload it through ECOMP, which gives you a tracking number. The CA-17 is the one that goes to the employer.
Can I write “low back pain” as the diagnosis on the CA-20?
No. The form says “pain” is not a compensable diagnosis. Name the condition in item 7 and put the pain in item 6 as a symptom of it.
Do I have to work out how much of the condition is due to work?
No. The form says there is no apportionment, so any contribution from work is covered. What you do have to do is explain, in item 9, how the work was enough to cause or worsen the diagnosis. A yes with no explanation is not accepted.
PatientPapers makes completing the CA-17 and CA-20 faster and easier
Every “gotcha” on that list is something software can catch before you sign. I created PatientPapers to make it easier and faster for you to complete this paperwork, because as a physician myself, I understand the burden of this paperwork and wanted to do something to decrease it. It is my own product, built through the same company as this site, so weigh this accordingly. It carries both OWCP forms, asks the causation question in the form’s own words, keeps “pain” out of the diagnosis box, and fills in the real form for you. You review it before you sign. The pricing and the full description are on the PatientPapers site.
Open PatientPapers